
What the 2025 AGA guideline says about when surgery is appropriate
The guideline is more conservative about procedures than most surgical marketing suggests, and I agree with it.
The AGA issued conditional recommendations against the routine initial use of gastric per-oral endoscopic pyloromyotomy and against the routine initial use of gastric electrical stimulation. Both are reserved for selected patients whose symptoms have not responded to optimized medical therapy, and both require shared decision-making rather than a default referral to the operating room.
Before procedures, the guideline supports dietary changes, specifically small-particle, low-fat, and low-residue eating, either before drug therapy or alongside it. For medication, it conditionally supports metoclopramide and erythromycin. It issued conditional recommendations against domperidone, prucalopride, aprepitant, nortriptyline, buspirone, and cannabidiol as first-line treatments.
The candidacy criteria for pyloromyotomy are specific enough to check yourself against. The guideline describes an appropriate candidate as someone with a gastroparesis diagnosis established by a properly performed 4-hour gastric emptying study, generally showing at least a moderate delay, plus six to twelve months of moderate cardinal symptoms. Those cardinal symptoms are nausea, vomiting, and postprandial fullness.
One more thing worth knowing, because it rarely appears on promotional pages. The AGA declined to issue any recommendation at all regarding surgical pyloromyotomy or surgical pyloroplasty, citing insufficient high-quality evidence to support a position for or against routine use. That is not the same as saying those operations do not work. It means the evidence base is thinner than the confidence with which they are sometimes offered.
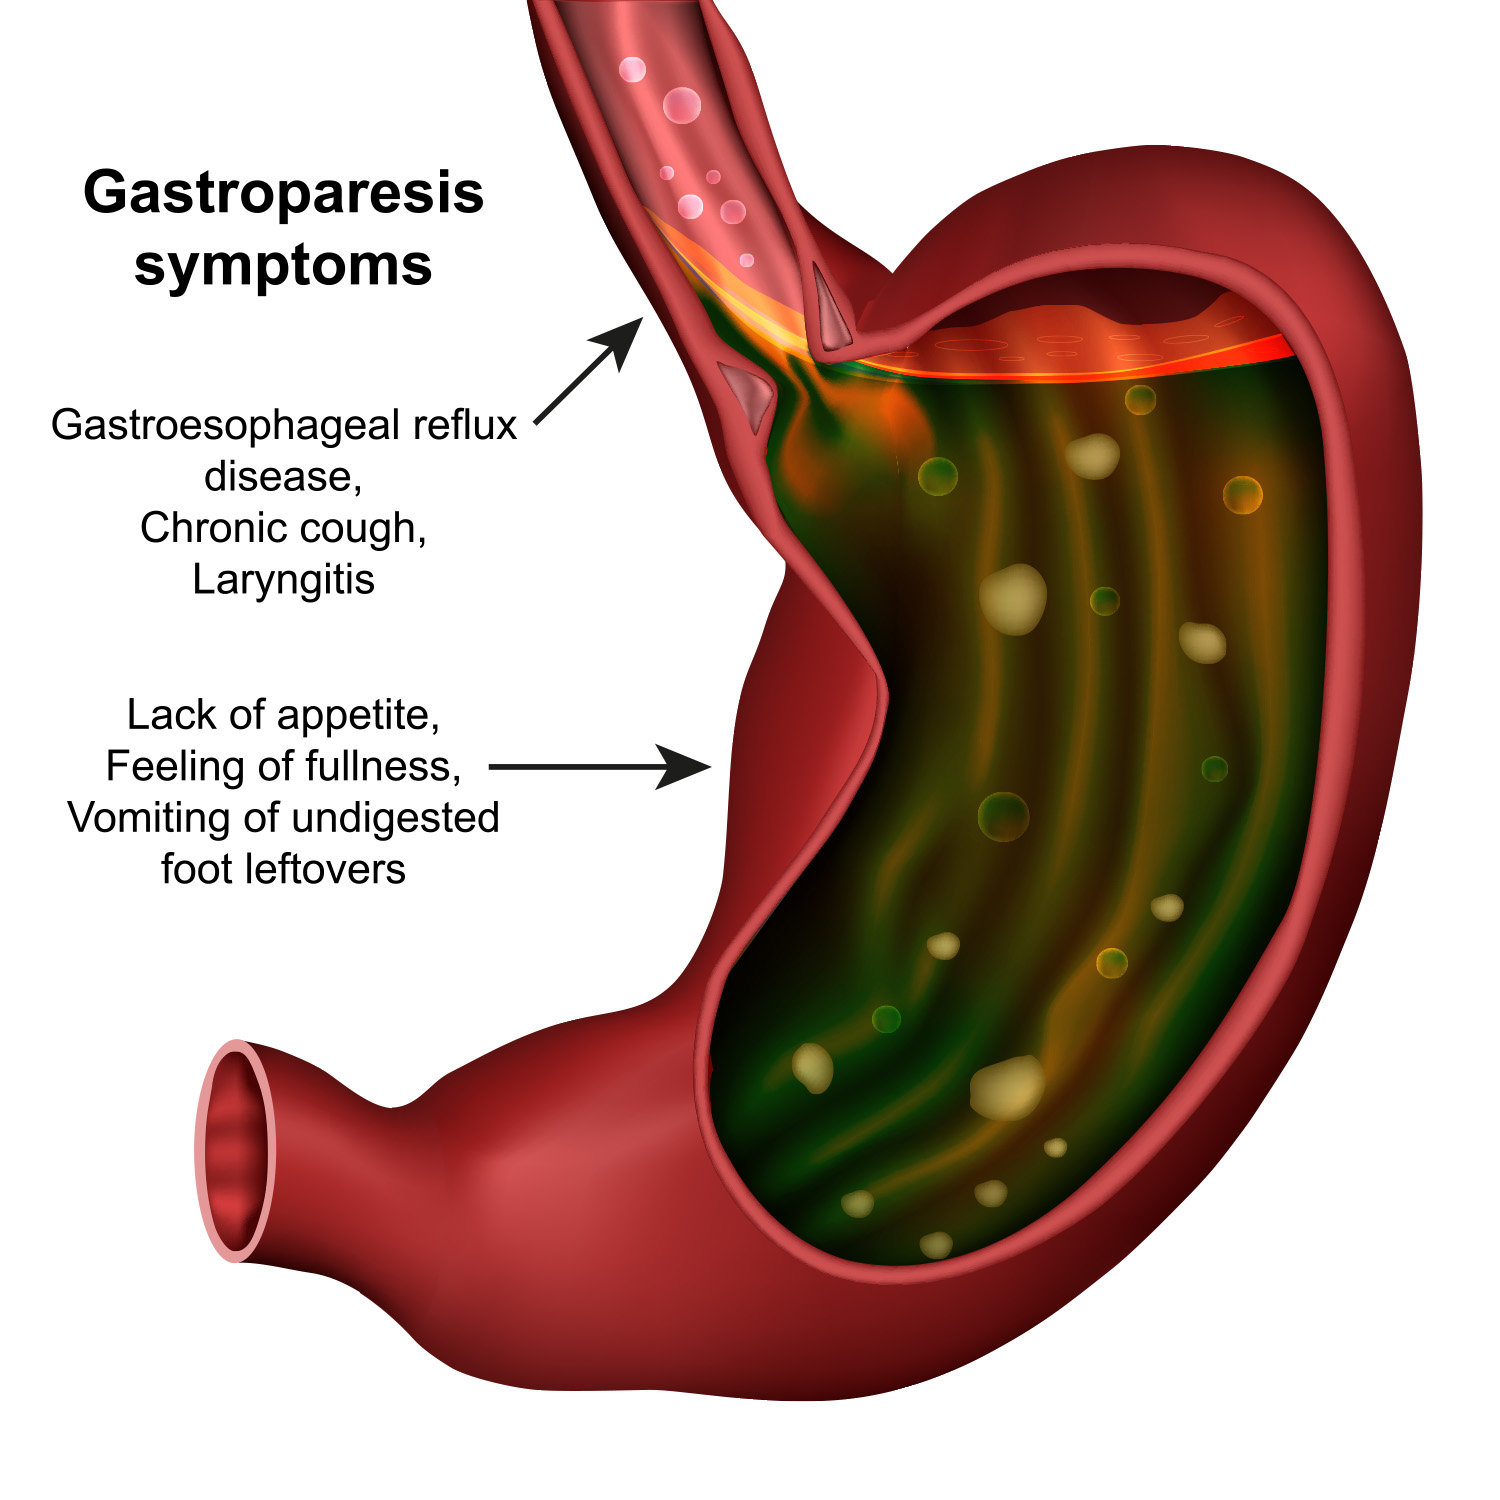

Endoscopic pyloromyotomy: the numbers, including the ones that get left out
Technical success for endoscopic pyloromyotomy runs above 95%. Clinical success is a different number, and it declines over time.
Short-term symptom improvement is reported in up to 80% of patients. Pooled one-year clinical success sits closer to 61%, with symptom recurrence accumulating at roughly 13% per year. Long-term studies at three to four years report sustained clinical success between 50% and 77.5%, with the spread driven largely by what caused the gastroparesis in the first place and how far the underlying neuromuscular disease has progressed.
Comparative data favors pyloromyotomy over botulinum toxin injection and over gastric electrical stimulation on both efficacy and durability, with fewer complications than surgical pyloroplasty. There is also evidence from 2025 suggesting that combining gastric electrical stimulation with pyloroplasty produces more durable symptom control than either approach alone, particularly in diabetic gastroparesis. That combination is a real option, and it is one reason I evaluate the whole picture before committing to a single procedure.
Patient selection is where the outcome is decided. The endoluminal functional lumen imaging probe, which measures how distensible the pylorus actually is, has shown promise for identifying who will respond. Standardized predictive thresholds still do not exist, so it informs judgment rather than replacing it. I use the same technology in a tailored approach when treating achalasia, where it has changed how precisely these decisions can be made.
I tell patients the same thing about this that I tell them about reflux surgery. The operation is the last step. The decision-making is the surgery.
The drug in late-stage trials that may change your timeline
If you are on the fence about a procedure, there is a reason to ask your gastroenterologist about the pipeline before you commit.
In May 2026, Dr. Falk Pharma and Renexxion announced results from MOVE-IT, a global Phase 2b randomized placebo-controlled trial of naronapride, an oral prokinetic that works through 5-HT4 receptor agonism combined with dopamine D2 receptor antagonism. The 12-week study enrolled 328 adults with moderate-to-severe idiopathic or diabetic gastroparesis and objective evidence of delayed emptying. Patients received 10, 20, or 40 mg three times daily, or placebo.
The trial met its primary endpoint. The 20 mg and 40 mg doses produced statistically significant symptom improvement versus placebo, with benefit reported across nausea, early satiety, postprandial fullness, and upper abdominal pain. In June 2026, the sponsors announced they are advancing naronapride into Phase 3 registration studies with a US new drug application planned on the results.
This is not an approved treatment and it is not available to you today. It matters for a different reason. Existing prokinetic options are limited, and metoclopramide carries an FDA black box warning that constrains long-term use. If a new oral agent reaches approval, the calculus for a patient with moderate symptoms and moderate delay shifts. For a patient with severe refractory disease and years of failed therapy, it does not.
Knowing which of those two patients you are is worth a consultation before you decide anything.
What the process looks like from Wesley Chapel
Two visits from first consultation to surgery, and four to eight weeks total. That is the structure, and it holds for out-of-area patients.
Send your records before you come. Prior upper endoscopy and pathology reports, any pH testing, esophageal manometry results, barium swallow or gastric emptying imaging, office notes from your gastroenterologist and any ENT, pulmonary, or allergy physicians, plus a current medication list and surgical history. Email them to info@tampareflux.com and I review every page personally before you walk in. Patients who do this get a diagnostic visit instead of a data-gathering visit.
New patients are typically seen within two weeks and always within four.
If your testing is already complete, one consultation is usually enough. Diagnosis is confirmed at that visit, options are discussed, and insurance authorization begins immediately. Surgery can be scheduled as early as four weeks out.
If testing is incomplete, the first visit covers education, record review, and test planning. Studies are ordered and coordinated, and a second visit roughly four weeks later reviews results and finalizes the plan. That path runs closer to eight weeks.
For patients coming from Wesley Chapel and farther, my office arranges as much testing as possible near where you live so you are not driving to Tampa for every study. We work with a small number of testing sites we trust, which shortens scheduling and keeps test quality consistent. My team routinely coordinates travel logistics for patients arriving from Orlando, Sarasota, Naples, Fort Myers, Jacksonville, and out of state.
Insurance authorization is handled entirely by my office and is always secured before surgery is scheduled. Payers generally require documentation of persistent symptoms despite medical therapy, objective testing confirming the diagnosis, and correlation between symptoms and test findings. Authorization can take four to six weeks in complex cases, and it frequently proceeds in parallel with testing rather than after it. Patients who call their own insurance company to help usually slow this down, because we already know what each payer wants and how to submit it.
The office is a yellow brick building at 1315 South Howard Avenue, next to Sally O’Neill’s Pizza, and parking is behind the pizza restaurant. All of my procedures are performed at HCA South Tampa Hospital. My physician assistant assists in every surgical case, knows your anatomy and your operation specifically, and is reachable during recovery. After hours, you can reach me directly.
Frequently asked questions
About Dr. Gopal Grandhige
I have practiced foregut surgery in Tampa Bay since 2009, and I founded Tampa Bay Reflux Center in 2009 and Tampa Bay Reflux Institute in 2022. My practice is limited to benign conditions of the esophagus, diaphragm, and stomach.
I completed my undergraduate degree in biology at Johns Hopkins University and my medical degree at the University of Michigan, Ann Arbor. My general surgery residency, my critical care fellowship, and my fellowship in foregut and minimally invasive surgery were all completed at Yale New Haven Hospital. I am a Fellow of the American College of Surgeons, a member of the Society of American Gastrointestinal and Endoscopic Surgeons, and a founding member of the American Foregut Society.
You can verify my board certification through the American Board of Surgery physician lookup and my active license through the Florida Department of Health Medical Quality Assurance license search. I hold privileges at St. Joseph’s Main Hospital, St. Joseph’s South Hospital, HCA Brandon Hospital, and HCA South Tampa Hospital, and I perform all surgeries at HCA South Tampa. More about the practice and how I evaluate foregut disease, and the full overview of how we approach gastroparesis, are available on our site.
The most important skill in this field is knowing when not to operate, and which operation not to do.



An endoscopy cannot tell you if you have reflux. It can only tell you if you have complications of GERD.
If you are unhappy with your reflux symptoms, come in and we can discuss testing and treatments that can accurately diagnose your problem.
#reflux #gerd #hiatalhernia #gastroparesis #linx


CALL US AT 813-922-2920
www.tampareflux.com
If you have a hiatal hernia and fit one of these categories, you should know your options.
Dr. Grandhige is an expert in his field and performs 200 of these surgeries a year. He is the only surgeon in the Tampa Bay Area who offers all surgical options - LINX, Fundoplications, TIF and will be one of 20 surgeons in America introducing the latest procedure RefluxStop in 2026.
We accept most insurances but will verify yours before you come in. These procedures are considered medically necessary and covered by your insurance. You can expect to pay your in-network deductibles and nothing else.
#hiatalhernia #reflux #GERD #LINX #refluxstop

What causes reflux ?
1. Weak lower esophageal sphincter
2. Hiatal hernia
3. Flattening of the Angle of His
4. Poor esophageal motility
5. Gastroparesis (slow stomach)
NOT increased acid production


Don’t let GERD get in the way of living your life. Request your appointment with us today on the link below.
.
.
.
.
https://tampareflux.com/contact-us/

Anyone can be victim to GERD and though weight loss can help reduce GERD symptoms. Many athletes with high impact workouts may continue to have these symptoms. This may be a symptom of a hiatal hernia or other issue. We are more then happy to assist you in finding your solution, just click the link below.
.
.
.
https://tampareflux.com/contact-us/
##healthylifestyle #workout #athletereflux #PPIs #heartburn #LINX #fundoplication #TIF #GERD#tampaheartburn #linx #TIF #fundoplication #tampabayreflux #GERD #acidreflux #acidrefluxsurgery #stopreflux
#nonsurgicalweightloss #ESG #gastricballoon #weightlossjourney #vsg #vsgjourney #spatz3 #orbera #orberaballoon #grandhige #DrG
#tampabayrefluxinstitute #guthealth #roboticsurgery

Heartburn may seem like an annoyance. But if you find yourself having symptoms on a daily basis, it may be time to to talk to Dr. Grandhige as it could be a symptom of something worse.
.
.
.
#chronicheartburn #gerdsymptoms #heartburnrelief #reflux #PPIs #heartburn #LINX #fundoplication #TIF #GERD#tampaheartburn #linx #TIF #fundoplication #tampabayreflux #GERD #acidreflux #acidrefluxsurgery #stopreflux
#nonsurgicalweightloss #ESG #gastricballoon #weightlossjourney #vsg #vsgjourney #spatz3 #orbera #orberaballoon #grandhige #DrG
#tampabayrefluxinstitute #guthealth #roboticsurgery

If you are tired of avoiding your favorite foods or taking daily medications, we can help.
We are the Tampa experts in reflux ! With years of experience and thousands of patients treated successfully, we offer all FDA approved anti-reflux procedures.
Call 813-922-2920 to schedule your appointment
All major insurances accepted.

Not all patients need surgical intervention. Many patients are living a heartburn free life with their PPIs. However 40% of patients taking PPIs are not getting the relief they need. If you are one of those, you have options! Come in and find out more.
.
.
.
.
#letushelpyou #medsnotworking #reflux #PPIs #heartburn #LINX #fundoplication #TIF #GERD#tampaheartburn #linx #TIF #fundoplication #tampabayreflux #GERD #acidreflux #acidrefluxsurgery #stopreflux
#nonsurgicalweightloss #ESG #gastricballoon #weightlossjourney #vsg #vsgjourney #spatz3 #orbera #orberaballoon #grandhige #DrG
#tampabayrefluxinstitute #guthealth #roboticsurgery

#heartburn #stopreflux #hiatalherniarepair #severeheartburn #reflux #tampabayreflux #acidrefluxsurgery #tampaheartburn #GERD #PPIs #achalasia #LINX #TIF #tampareflux #fundoplication #stomach #digestivehealth #ESG #obesity #overweight #weightlossjourney #gastricballoon
