
When a hiatal hernia needs repair, and how I decide
I recommend repair in four situations.
Any hernia larger than 3 centimeters. At that size it is almost always contributing mechanically to reflux, medication will not manage it, and it tends to keep growing. Large hernias carry a risk of gastric volvulus, and the bigger they get, the more likely the stomach becomes atonic, which may not recover even after repair.
Any hernia paired with real reflux symptoms, particularly regurgitation. Even a small hernia produces major symptoms once the sphincter is also failing.
Any hernia with complications of reflux. Severe esophagitis, Barrett’s esophagus or a peptic stricture changes the calculation.
Any hernia found during a workup for reflux surgery. Repairing it is what makes the rest of the operation durable.
Almost every patient with reflux has a hiatal hernia, including plenty too small for endoscopy to see. It matters because the reflux barrier has two parts: the lower esophageal sphincter and the diaphragm. Picture a two-part door. If one fails you get reflux. If both fail, reflux is close to inevitable. Fixing half of a two-part problem is one of the most common reasons reflux treatment fails. My criteria sit alongside the SAGES evidence-based guidelines for the surgical treatment of hiatal hernias, worth reading before any consultation.
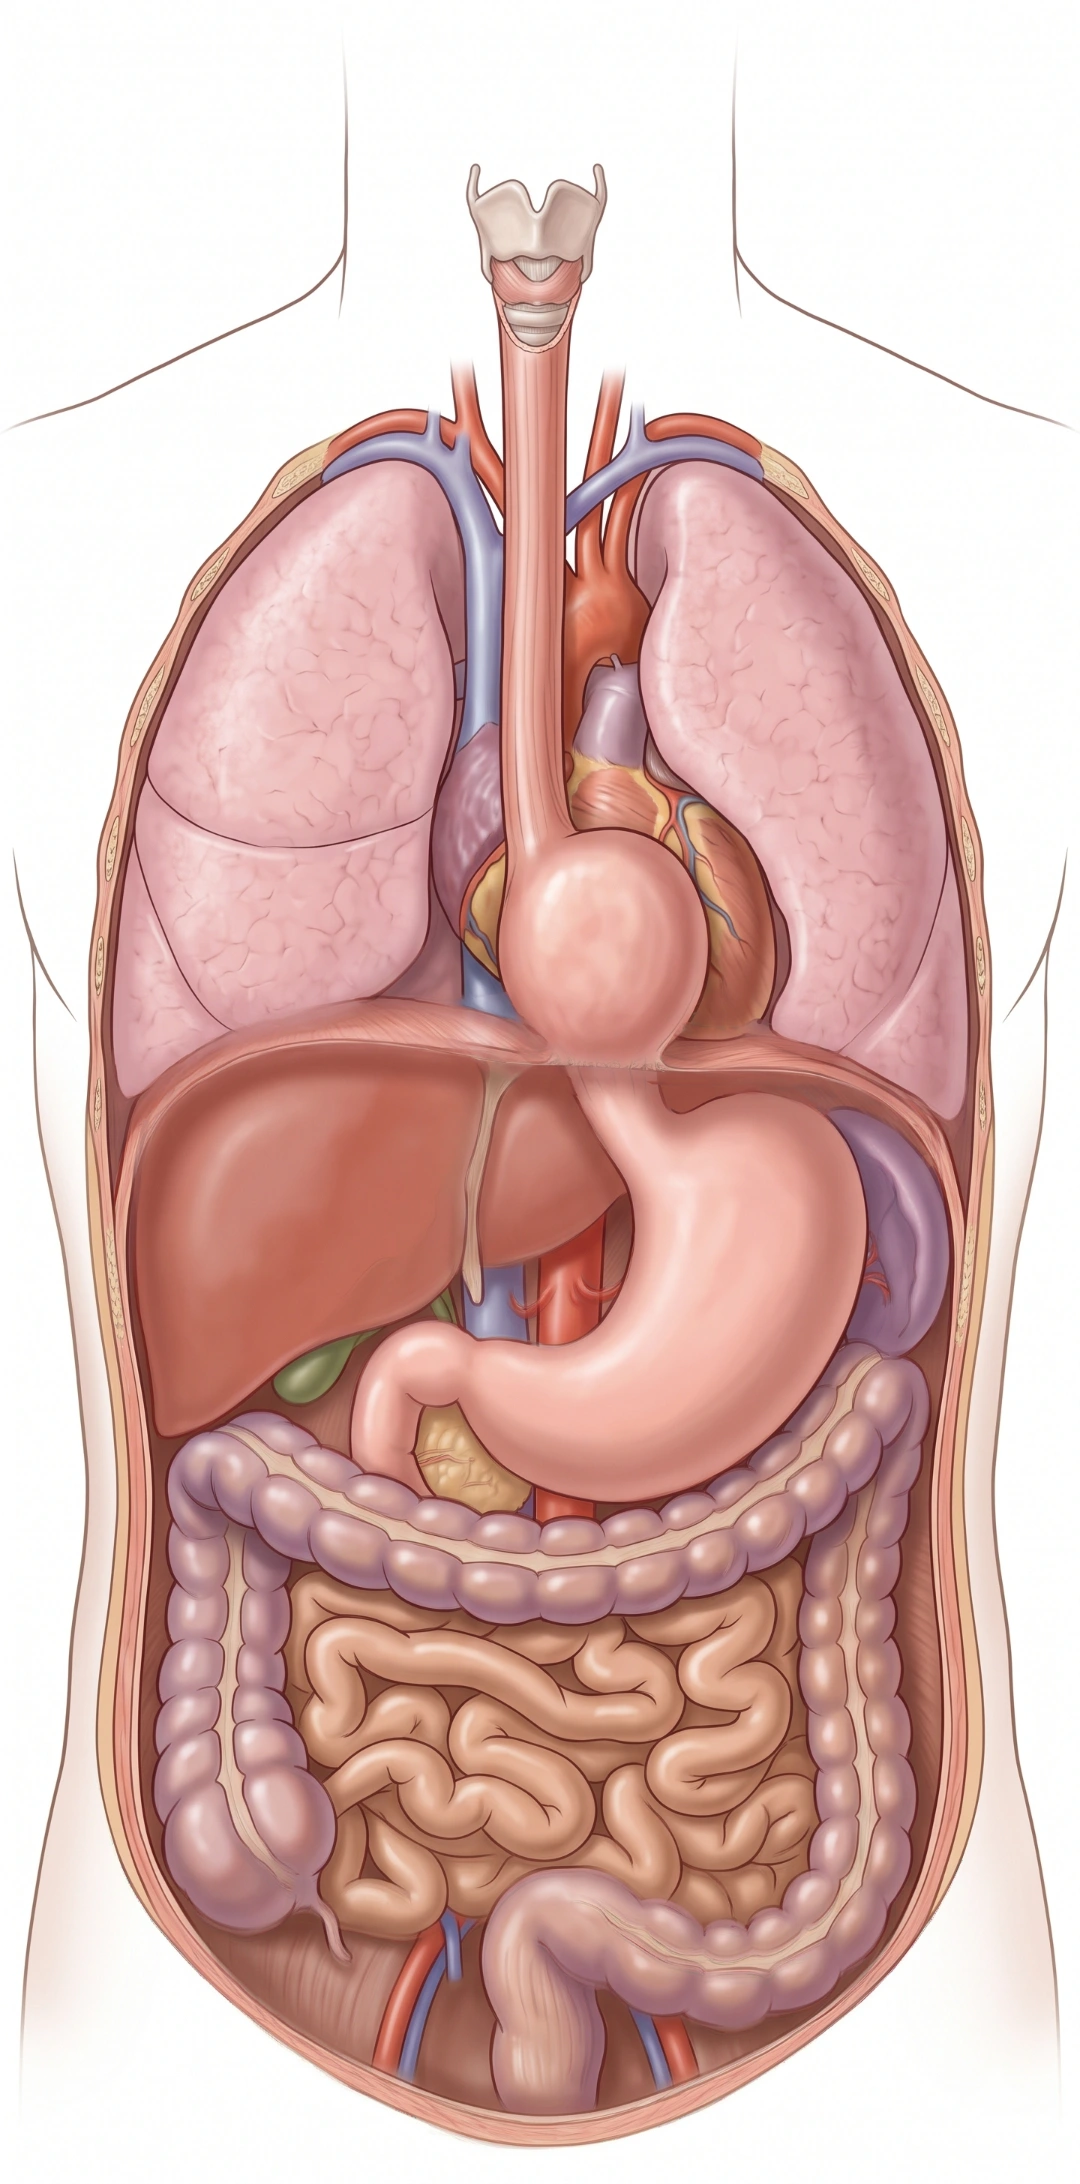
The Six-Step Repair Sequence
Meeting one of those criteria opens the conversation. It does not book an operating room. Every patient runs the same sequence, in order, and it can stop at any step.
1. Prove the reflux is real. Objective pH testing, correlation of reflux events against your actual symptoms, and identification of whether the reflux is acid, non-acid or bile. No objective reflux, no surgery, however convincing the symptoms.
2. Map the anatomy. Hernia size, esophageal length and position, and the relationship between stomach, diaphragm and esophagus. This determines which repairs are technically possible and how long each will last.
3. Measure esophageal function. Manometry gives me contraction strength, swallowing coordination, and whether spasm or a motility disorder is present. Most overlooked factor in the decision. Ignoring motility produces dysphagia and regret.
4. Sort the symptoms. What is very likely reflux, what is unlikely, what may be multifactorial. Patients want one diagnosis to explain everything. Bodies do not work that way.
5. Weigh your priorities. Durability, getting off medication, keeping the ability to burp and vomit, side effects, reversibility. Preferences refine the decision once medical appropriateness is settled. They never override anatomy or physiology.
6. Choose a repair, or choose none. Observation and medical management stay on the table through the final step.
The operation is the last step. The decision-making is the surgery.
The four repairs I perform, and who each one fits
The hernia repair is similar in every case. The stomach comes back down into the abdomen, the esophagus returns below the diaphragm, and the diaphragmatic opening is closed and reinforced. What changes is what goes on top, and that choice is where results are won or lost.
Fundoplication
Fundoplication wraps your own stomach tissue around the lower esophagus to reinforce the failing valve. It does not stop acid production. It stops acid going where it does not belong.
It is not one operation. I perform Nissen (a full 360-degree wrap), Toupet (posterior 270), Watson (anterior 270) and Dor (anterior partial). Configuration is chosen before surgery from your manometry results, because a weaker esophagus needs a partial wrap it can push food through. The procedure runs 1.5 to 2 hours, laparoscopic or robotic, and most patients go home the same day. Diet progresses over 2 to 3 months.
Fundoplication handles large hernias, carries decades of outcome data and is the most durable option. The honest trade-off is gas-bloat and a reduced ability to burp or vomit, temporary or permanent depending on the configuration.
LINX
LINX is a ring of magnetic titanium beads placed around the lower esophagus. It does not raise the resting pressure of your sphincter. It resists opening when pressure inside the stomach rises, then opens when you swallow.
Most patients keep the ability to burp and vomit once early inflammation settles, so bloating is less of a problem. Stomach anatomy stays untouched and the device can be removed later without closing off future options. Hernia size does not disqualify you, which surprises people. What matters is that the hernia gets repaired at the same operation.
Two honest limits. LINX needs good esophageal motility, because your esophagus has to push food through the resistance, so early swallowing difficulty is more common and a small long-term risk exists. Current devices are MRI compatible up to 1.5 Tesla. One pattern I see across hundreds of cases and rarely hear discussed: patients highly attuned to internal sensation tend to sense the device. If you felt the Bravo pH capsule while it was in place, you will probably feel your LINX.
TIF
TIF, performed with the EsophyX device, goes entirely through the mouth with an endoscope. No abdominal incisions, general anesthesia, 45 to 60 minutes, home the same day.
TIF cannot repair a hiatal hernia. It does not touch the diaphragm. It modifies sphincter mechanics only, which is why its reputation is mixed and why it is right for a narrow group: no hernia or a very small one, mild to moderate reflux, no Barrett’s esophagus, no severe esophagitis, no stricture, and not obese. I quote a failure rate of 2% per year, roughly 20% per decade, and heavy lifting is restricted for 6 weeks. It is the best endoscopic anti-reflux procedure available, and it should be understood as a solution that works for years rather than a permanent one.
I decline to perform TIF outside those criteria even when patients request it. Choosing the least invasive option is not the same as choosing the right one.
RefluxStop, and what changed in 2026
RefluxStop is the fourth option, and the situation shifted this year. The FDA granted Premarket Approval on August 20, 2026, clearing the device for the U.S. market for the first time. You can read the manufacturer’s announcement of that approval directly. The U.S. launch began at the American Foregut Society meeting in late September 2026, a society I helped found.
The device holds the gastroesophageal junction in its natural position without encircling or compressing the esophagus, a different mechanism from either a wrap or a magnetic ring. U.S. availability is rolling out site by site, since each center requires surgeon training and activation, so call the office for current status rather than assuming from a webpage.
Adding RefluxStop makes me the only surgeon in the Tampa Bay area offering all four anti-reflux repairs. That matters for one reason: the recommendation you get is never limited by what I happen to be comfortable performing.
The patients I turn down
Some of my most grateful patients are the ones I refused to operate on. A technically perfect operation performed on the wrong patient is a failure.
Across LPR patients, roughly 50 to 60% have testing that supports surgery. The rest do not, and I tell them so. Among patients with typical heartburn and regurgitation, most who complete testing turn out to be candidates. If a surgeon tells you he never advises against operating, that is not confidence. It is an absence of diagnostic restraint.
I do not operate when reflux is not objectively proven, however severe the symptoms. I do not operate when the real driver is esophageal hypersensitivity, functional chest pain, rumination, or an ENT, pulmonary or allergy condition that resembles reflux. I do not place LINX in someone with a severe motility disorder. I do not perform TIF outside its criteria. I do not treat esophageal or gastric cancer. When surgery is not the answer, I hand patients directly to physicians I know personally, so nothing gets duplicated and the diagnosis does not get muddied.
Patients who came expecting a fix and leave without one are often the most frustrated people I see. They would be considerably more frustrated after an unnecessary operation that changed nothing.
Your timeline from Brandon: first call to surgery
Most patients are seen within 2 weeks of calling, always within 4. From first consultation to surgery, my target is 4 to 8 weeks. Where you land depends on whether your testing is already done.
Arrive with a completed endoscopy, pH study, manometry and relevant imaging, and one consultation is usually enough. I can often confirm the diagnosis that day, discuss options immediately and start authorization the same week. Surgery can be as soon as 4 weeks out.
If your testing is incomplete, plan on two visits roughly 4 weeks apart. The first covers education, record review and test planning. Testing runs through a small number of sites I work with regularly, which keeps quality consistent and results moving. The second visit reviews results and finalizes the plan. That path lands closer to 8 weeks.
You can compress this yourself. Email your records to info@tampareflux.com before your appointment: prior endoscopy and pathology reports, any pH testing including Bravo or catheter studies, manometry results, barium swallow or other imaging, office notes from your gastroenterologist, ENT, pulmonologist or allergist, a current medication list, and a list of prior surgeries. Signed record releases alone are not enough. Faxes get lost, systems do not talk to each other, and reports arrive with the critical data missing. Patients who bring their own records get definitive answers in one visit.
I read every page myself before your consultation. That is not delegated, and it is why the visit gets spent on explanation rather than data gathering. I will draw your anatomy for you on paper. Patients mention those drawings in reviews more than almost anything else.
After surgery, my physician assistant is involved in every case, knows your specific anatomy and operation, and is reachable during office hours. After hours and on weekends, you reach me directly. My office medical assistants have been here over a decade, so whoever answers your question has heard it before.

Questions Brandon patients ask before booking
The next step
You do not have to keep escalating medication and hoping. You also do not have to accept an operation you may not need.
Book a consultation and bring your records. If the testing says surgery will not help you, I will say so, and you will leave understanding your own body better than when you walked in. That is a successful visit.
Tampa Bay Reflux Institute 1315 South Howard Avenue, Suite 101, Tampa, FL 33606 Phone: 813-922-2920 Hours: 9:00 AM to 6:00 PM, Monday through Friday


An endoscopy cannot tell you if you have reflux. It can only tell you if you have complications of GERD.
If you are unhappy with your reflux symptoms, come in and we can discuss testing and treatments that can accurately diagnose your problem.
#reflux #gerd #hiatalhernia #gastroparesis #linx


CALL US AT 813-922-2920
www.tampareflux.com
If you have a hiatal hernia and fit one of these categories, you should know your options.
Dr. Grandhige is an expert in his field and performs 200 of these surgeries a year. He is the only surgeon in the Tampa Bay Area who offers all surgical options - LINX, Fundoplications, TIF and will be one of 20 surgeons in America introducing the latest procedure RefluxStop in 2026.
We accept most insurances but will verify yours before you come in. These procedures are considered medically necessary and covered by your insurance. You can expect to pay your in-network deductibles and nothing else.
#hiatalhernia #reflux #GERD #LINX #refluxstop

What causes reflux ?
1. Weak lower esophageal sphincter
2. Hiatal hernia
3. Flattening of the Angle of His
4. Poor esophageal motility
5. Gastroparesis (slow stomach)
NOT increased acid production


Don’t let GERD get in the way of living your life. Request your appointment with us today on the link below.
.
.
.
.
https://tampareflux.com/contact-us/

Anyone can be victim to GERD and though weight loss can help reduce GERD symptoms. Many athletes with high impact workouts may continue to have these symptoms. This may be a symptom of a hiatal hernia or other issue. We are more then happy to assist you in finding your solution, just click the link below.
.
.
.
https://tampareflux.com/contact-us/
##healthylifestyle #workout #athletereflux #PPIs #heartburn #LINX #fundoplication #TIF #GERD#tampaheartburn #linx #TIF #fundoplication #tampabayreflux #GERD #acidreflux #acidrefluxsurgery #stopreflux
#nonsurgicalweightloss #ESG #gastricballoon #weightlossjourney #vsg #vsgjourney #spatz3 #orbera #orberaballoon #grandhige #DrG
#tampabayrefluxinstitute #guthealth #roboticsurgery

Heartburn may seem like an annoyance. But if you find yourself having symptoms on a daily basis, it may be time to to talk to Dr. Grandhige as it could be a symptom of something worse.
.
.
.
#chronicheartburn #gerdsymptoms #heartburnrelief #reflux #PPIs #heartburn #LINX #fundoplication #TIF #GERD#tampaheartburn #linx #TIF #fundoplication #tampabayreflux #GERD #acidreflux #acidrefluxsurgery #stopreflux
#nonsurgicalweightloss #ESG #gastricballoon #weightlossjourney #vsg #vsgjourney #spatz3 #orbera #orberaballoon #grandhige #DrG
#tampabayrefluxinstitute #guthealth #roboticsurgery

If you are tired of avoiding your favorite foods or taking daily medications, we can help.
We are the Tampa experts in reflux ! With years of experience and thousands of patients treated successfully, we offer all FDA approved anti-reflux procedures.
Call 813-922-2920 to schedule your appointment
All major insurances accepted.

Not all patients need surgical intervention. Many patients are living a heartburn free life with their PPIs. However 40% of patients taking PPIs are not getting the relief they need. If you are one of those, you have options! Come in and find out more.
.
.
.
.
#letushelpyou #medsnotworking #reflux #PPIs #heartburn #LINX #fundoplication #TIF #GERD#tampaheartburn #linx #TIF #fundoplication #tampabayreflux #GERD #acidreflux #acidrefluxsurgery #stopreflux
#nonsurgicalweightloss #ESG #gastricballoon #weightlossjourney #vsg #vsgjourney #spatz3 #orbera #orberaballoon #grandhige #DrG
#tampabayrefluxinstitute #guthealth #roboticsurgery

#heartburn #stopreflux #hiatalherniarepair #severeheartburn #reflux #tampabayreflux #acidrefluxsurgery #tampaheartburn #GERD #PPIs #achalasia #LINX #TIF #tampareflux #fundoplication #stomach #digestivehealth #ESG #obesity #overweight #weightlossjourney #gastricballoon
