
The Four Tests, and the Question Each One Answers
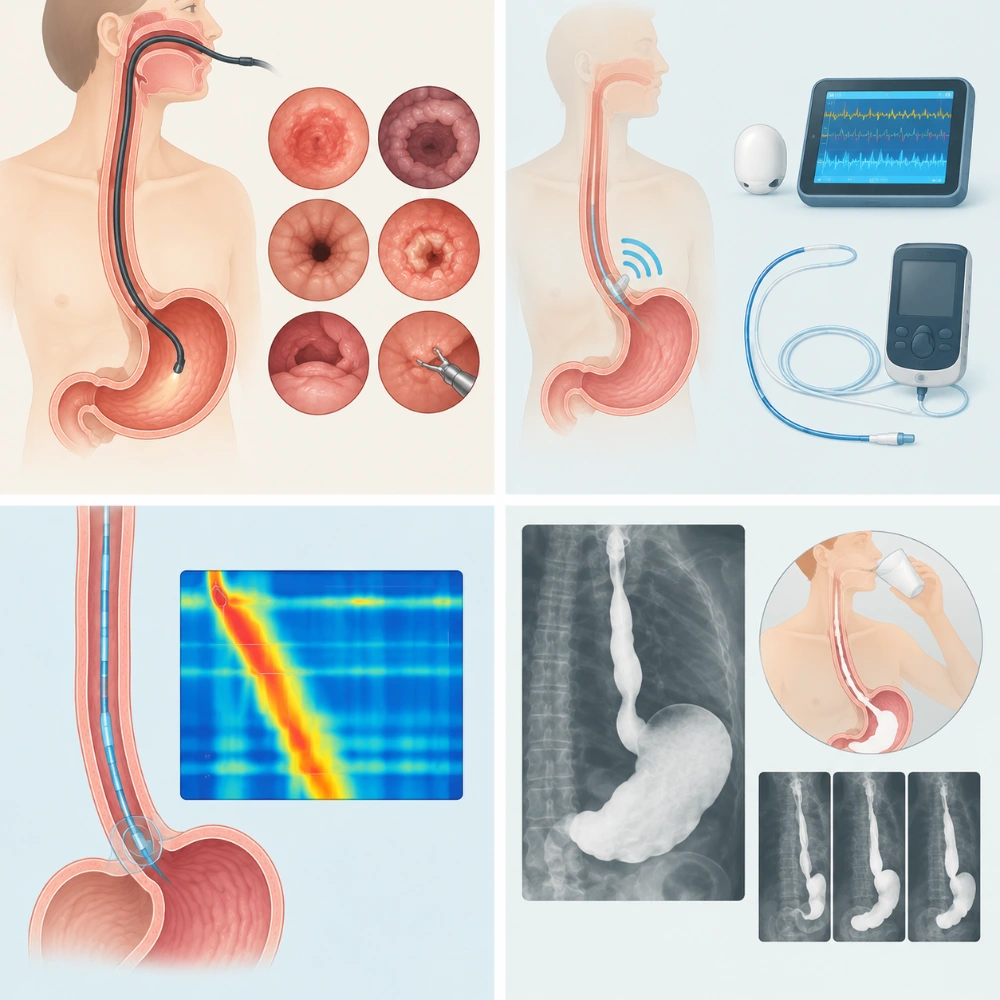
Each test answers a different question, and skipping one leaves a gap that shows up later as a poor outcome.
Upper endoscopy shows damage. It identifies esophagitis, Barrett’s esophagus, ulcers, strictures, and visible hernias, and it allows biopsies. It does not measure reflux events and it does not assess sphincter function. A normal endoscopy does not rule out reflux, and small hiatal hernias are not visible on every endoscopy.
pH monitoring answers whether reflux is actually occurring. Using a wireless Bravo capsule or a catheter-based probe, the study records 48 to 72 hours of ordinary life: eating, working, exercising, sleeping. It measures how often reflux happens, how long each episode lasts, how acidic it is, when it occurs, and whether your symptoms line up with the events.
Esophageal manometry answers whether your esophagus can handle a repair. It measures contraction strength, swallow coordination, and sphincter relaxation, and it identifies achalasia, esophageal spasm, ineffective motility, jackhammer and nutcracker esophagus, and a hypertensive sphincter. Every anti-reflux procedure adds resistance at the gastroesophageal junction, so a weak esophagus given a full wrap produces swallowing trouble that is far harder to fix afterward than to prevent.
Barium swallow answers what happens when you actually swallow, and it is used selectively. It is ordered for dysphagia, suspected strictures, prior foregut surgery, checking LINX position, or when findings disagree with each other. It reveals something most patients find surprising: where you feel food sticking matches where it is actually sticking only about 60 percent of the time. Patients regularly point to the throat when the delay is in the distal esophagus.
Silent Reflux Needs a Different Test Entirely
The esophagus can tolerate 40 to 50 reflux episodes a day. The larynx and pharynx can produce symptoms from a single one. That difference explains why silent reflux gets missed so often, and why standard testing does not settle it.
Standard reflux studies measure exposure above the lower esophageal sphincter only. Dr. Grandhige uses a customized 24-hour dual-channel pH impedance probe that measures above the lower esophageal sphincter and above the upper esophageal sphincter, and the impedance component captures non-acid reflux, including bile, pepsin, and trypsin, that pH testing alone cannot see.
The difference this makes is measurable. Patients with laryngopharyngeal reflux are commonly quoted roughly a 50 percent chance that surgery will help. Selecting patients with dual-channel testing raises expected symptom improvement to approximately 80 percent. Testing also disqualifies people. Around 50 to 60 percent of LPR patients who undergo this evaluation turn out to have findings that warrant a procedure. The rest are told directly that surgery is not the answer for them.
What Changed in August 2026: RefluxStop Reached the U.S. Market
The FDA granted premarket approval for the RefluxStop device on August 20, 2026, under PMA number P250018. Any page still describing it as unavailable in the United States is out of date.
RefluxStop works differently from the other three. The implant sits outside the stomach, covered by a pouch of stomach wall, and holds the gastroesophageal junction in its correct position below the diaphragm. It does not wrap the esophagus and it does not narrow the food passage, which is why it is of particular interest for patients with weak esophageal motility.
One detail in the approval deserves attention from anyone weighing this option. The FDA indication itself defines the eligible patient as someone diagnosed with GERD by abnormal impedance pH or pH testing. The regulator wrote the testing requirement into the label. That is the same standard Dr. Grandhige has applied to every reflux patient since 2009.
Availability will not be immediate everywhere. The manufacturer has stated that the U.S. launch will be targeted at selected centers and reflux surgeons first, with adoption building gradually as surgeons are trained and individual sites are activated. Tampa Bay Reflux Institute plans to add RefluxStop, which would bring all four major anti-reflux procedures under one surgeon here.
Why Case Volume Changes Your Odds
Where an elective hiatal hernia repair is performed measurably affects the outcome, and there is national data on exactly how much.
A study published in Annals of Surgery Open in December 2025 examined 13,658 elective hiatal hernia repairs performed at 174 centers in the Society of Thoracic Surgeons General Thoracic Surgery Database between 2018 and 2023. Centers were sorted into thirds by annual case volume. Thirty-day complication rates fell in steps across those thirds: 22.4 percent at the lowest-volume centers, 18.4 percent in the middle, and 14.0 percent at the highest-volume centers. Reoperation rates followed the same pattern, at 4.7 percent, 2.7 percent, and 1.7 percent. The differences held after adjusting for patient factors, and the authors recommended referral to high-volume centers for elective repairs.
That is national data, not this practice’s own numbers, and it is worth reading for what it does say. An elective repair is elective. You have time to choose where it happens, and a short difference in drive time is a small price against a measurable difference in reoperation risk.
On this practice’s own results: for patients with typical reflux symptoms who have objective evidence of reflux, appropriate anatomy, and good esophageal function, Tampa Bay Reflux Institute reports greater than 95 percent success in significant symptom relief, elimination of daily reflux medication, and patient satisfaction. Those numbers apply to that group. Outcomes are lower, and are discussed individually, for patients with reduced esophageal motility, long-standing or recurrent disease, large hernias, prior foregut surgery, or prior bariatric surgery. No procedure has a 100 percent success rate, and some symptoms are driven by more than one cause.
Your Surgeon, and Where Your Surgery Happens
Gopal Grandhige, MD, FACS has practiced foregut surgery exclusively in Tampa Bay since 2009. He holds surgical privileges at HCA Brandon Hospital, St. Joseph’s Main Hospital, St. Joseph’s South Hospital, and HCA South Tampa Hospital.
All foregut and reflux operations are performed at HCA South Tampa Hospital. Brandon patients should know that up front. The reason is consistency: the same operating room team, the same anesthesiologists, the same surgical technologists, the same equipment setup, and the same physician assistant in every single case. Anesthesia matters more here than most patients expect, because postoperative vomiting is associated with early failure of a hiatal hernia repair, and a team that manages foregut cases routinely prevents that rather than reacting to it.
His training is listed on the practice’s about page: a Bachelor of Science in Biology from Johns Hopkins University, a medical degree from the University of Michigan, general surgery residency at Yale-New Haven Hospital, a fellowship in burn and critical care at Yale-New Haven, and a fellowship in foregut and minimally invasive surgery at Yale-New Haven. He is a board-certified general surgeon, a Fellow of the American College of Surgeons, a member of the Society of American Gastrointestinal and Endoscopic Surgeons, and a founding member of the American Foregut Society. He founded Tampa Bay Reflux Center in 2009 and Tampa Bay Reflux Institute in 2022. Board certification can be verified through the American Board of Surgery and licensure through the Florida Department of Health.
The office is at 1315 South Howard Avenue, Suite 101, Tampa, FL 33606, in the yellow brick building next to Sally O’Neill’s Pizza, with parking behind the restaurant. From Brandon, the Selmon Expressway runs most of the way. Phone 813.922.2920. Hours are 9 a.m. to 6 p.m., Monday through Friday. The medical assistants who answer that phone have worked with Dr. Grandhige for over a decade and know reflux well enough to answer most questions on the first call.

Frequently Asked Questions
Get an answer instead of another prescription.
If you are on daily or twice-daily medication and still have symptoms, if you were told your endoscopy was normal but something is clearly wrong, or if you were told you have a hiatal hernia and nobody explained what that means for you, the next step is objective testing and a clear explanation of what it shows. Some patients arrive expecting surgery and leave with a non-surgical plan. Others arrive skeptical and leave understanding exactly why a specific procedure fits their anatomy. Either outcome counts as a successful consultation.
Tampa Bay Reflux Institute serves Brandon, Riverview, Valrico, Seffner, Lithia, and the surrounding communities from its South Tampa office.


An endoscopy cannot tell you if you have reflux. It can only tell you if you have complications of GERD.
If you are unhappy with your reflux symptoms, come in and we can discuss testing and treatments that can accurately diagnose your problem.
#reflux #gerd #hiatalhernia #gastroparesis #linx


CALL US AT 813-922-2920
www.tampareflux.com
If you have a hiatal hernia and fit one of these categories, you should know your options.
Dr. Grandhige is an expert in his field and performs 200 of these surgeries a year. He is the only surgeon in the Tampa Bay Area who offers all surgical options - LINX, Fundoplications, TIF and will be one of 20 surgeons in America introducing the latest procedure RefluxStop in 2026.
We accept most insurances but will verify yours before you come in. These procedures are considered medically necessary and covered by your insurance. You can expect to pay your in-network deductibles and nothing else.
#hiatalhernia #reflux #GERD #LINX #refluxstop

What causes reflux ?
1. Weak lower esophageal sphincter
2. Hiatal hernia
3. Flattening of the Angle of His
4. Poor esophageal motility
5. Gastroparesis (slow stomach)
NOT increased acid production


Don’t let GERD get in the way of living your life. Request your appointment with us today on the link below.
.
.
.
.
https://tampareflux.com/contact-us/

Anyone can be victim to GERD and though weight loss can help reduce GERD symptoms. Many athletes with high impact workouts may continue to have these symptoms. This may be a symptom of a hiatal hernia or other issue. We are more then happy to assist you in finding your solution, just click the link below.
.
.
.
https://tampareflux.com/contact-us/
##healthylifestyle #workout #athletereflux #PPIs #heartburn #LINX #fundoplication #TIF #GERD#tampaheartburn #linx #TIF #fundoplication #tampabayreflux #GERD #acidreflux #acidrefluxsurgery #stopreflux
#nonsurgicalweightloss #ESG #gastricballoon #weightlossjourney #vsg #vsgjourney #spatz3 #orbera #orberaballoon #grandhige #DrG
#tampabayrefluxinstitute #guthealth #roboticsurgery

Heartburn may seem like an annoyance. But if you find yourself having symptoms on a daily basis, it may be time to to talk to Dr. Grandhige as it could be a symptom of something worse.
.
.
.
#chronicheartburn #gerdsymptoms #heartburnrelief #reflux #PPIs #heartburn #LINX #fundoplication #TIF #GERD#tampaheartburn #linx #TIF #fundoplication #tampabayreflux #GERD #acidreflux #acidrefluxsurgery #stopreflux
#nonsurgicalweightloss #ESG #gastricballoon #weightlossjourney #vsg #vsgjourney #spatz3 #orbera #orberaballoon #grandhige #DrG
#tampabayrefluxinstitute #guthealth #roboticsurgery

If you are tired of avoiding your favorite foods or taking daily medications, we can help.
We are the Tampa experts in reflux ! With years of experience and thousands of patients treated successfully, we offer all FDA approved anti-reflux procedures.
Call 813-922-2920 to schedule your appointment
All major insurances accepted.

Not all patients need surgical intervention. Many patients are living a heartburn free life with their PPIs. However 40% of patients taking PPIs are not getting the relief they need. If you are one of those, you have options! Come in and find out more.
.
.
.
.
#letushelpyou #medsnotworking #reflux #PPIs #heartburn #LINX #fundoplication #TIF #GERD#tampaheartburn #linx #TIF #fundoplication #tampabayreflux #GERD #acidreflux #acidrefluxsurgery #stopreflux
#nonsurgicalweightloss #ESG #gastricballoon #weightlossjourney #vsg #vsgjourney #spatz3 #orbera #orberaballoon #grandhige #DrG
#tampabayrefluxinstitute #guthealth #roboticsurgery

#heartburn #stopreflux #hiatalherniarepair #severeheartburn #reflux #tampabayreflux #acidrefluxsurgery #tampaheartburn #GERD #PPIs #achalasia #LINX #TIF #tampareflux #fundoplication #stomach #digestivehealth #ESG #obesity #overweight #weightlossjourney #gastricballoon
